
Advertisement
Clinical Research and Public HealthClinical ResearchHematologyOncology
Open Access |  10.1172/JCI207391
A single-arm prospective phase I trial of 68Ga-PFBC01 PET/CT for multiple myeloma B cell maturation antigen imaging
Tingfei Gu,1 Zhao Chen,1 Bo Tang,2 Tianyao Wang,1 Qi Yang,1 Huihui Liu,2 Zeyin Liang,2 Qian Wang,2 Yang Zhang,2 Yuhua Sun,2 Mingyi Di,2 Tingting Yuan,1 Yongkang Qiu,1 Yimeng Du,3 Lele Song,1 Shengnan Wu,1 Wei Wang,4 Xiaojie Xu,3 Yujun Dong,2 and Lei Kang1
1Department of Nuclear Medicine and
2Department of Hematology, Peking University First Hospital, Beijing, China.
3Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing, China.
4Department of Pathology, Peking University First Hospital, Beijing, China.
Address correspondence to: Lei Kang or Yujun Dong, Department of Nuclear Medicine, Peking University First Hospital, No. 8 Xishiku Str., Xicheng Dist, Beijing, 100034, China. Phone: 86.10.83575252; Email: kanglei@bjmu.edu.cn (LK); dongy@hsc.pku.edu.cn (YD). Or to: Xiaojie Xu, Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing100071, China. Email: miraclexxj@126.com.
Authorship note: TG, ZC, BT, TW, and QY contributed equally to this work.
Find articles by Gu, T. in: PubMed | Google Scholar
1Department of Nuclear Medicine and
2Department of Hematology, Peking University First Hospital, Beijing, China.
3Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing, China.
4Department of Pathology, Peking University First Hospital, Beijing, China.
Address correspondence to: Lei Kang or Yujun Dong, Department of Nuclear Medicine, Peking University First Hospital, No. 8 Xishiku Str., Xicheng Dist, Beijing, 100034, China. Phone: 86.10.83575252; Email: kanglei@bjmu.edu.cn (LK); dongy@hsc.pku.edu.cn (YD). Or to: Xiaojie Xu, Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing100071, China. Email: miraclexxj@126.com.
Authorship note: TG, ZC, BT, TW, and QY contributed equally to this work.
Find articles by Chen, Z. in: PubMed | Google Scholar
1Department of Nuclear Medicine and
2Department of Hematology, Peking University First Hospital, Beijing, China.
3Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing, China.
4Department of Pathology, Peking University First Hospital, Beijing, China.
Address correspondence to: Lei Kang or Yujun Dong, Department of Nuclear Medicine, Peking University First Hospital, No. 8 Xishiku Str., Xicheng Dist, Beijing, 100034, China. Phone: 86.10.83575252; Email: kanglei@bjmu.edu.cn (LK); dongy@hsc.pku.edu.cn (YD). Or to: Xiaojie Xu, Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing100071, China. Email: miraclexxj@126.com.
Authorship note: TG, ZC, BT, TW, and QY contributed equally to this work.
Find articles by Tang, B. in: PubMed | Google Scholar
1Department of Nuclear Medicine and
2Department of Hematology, Peking University First Hospital, Beijing, China.
3Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing, China.
4Department of Pathology, Peking University First Hospital, Beijing, China.
Address correspondence to: Lei Kang or Yujun Dong, Department of Nuclear Medicine, Peking University First Hospital, No. 8 Xishiku Str., Xicheng Dist, Beijing, 100034, China. Phone: 86.10.83575252; Email: kanglei@bjmu.edu.cn (LK); dongy@hsc.pku.edu.cn (YD). Or to: Xiaojie Xu, Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing100071, China. Email: miraclexxj@126.com.
Authorship note: TG, ZC, BT, TW, and QY contributed equally to this work.
Find articles by Wang, T. in: PubMed | Google Scholar
1Department of Nuclear Medicine and
2Department of Hematology, Peking University First Hospital, Beijing, China.
3Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing, China.
4Department of Pathology, Peking University First Hospital, Beijing, China.
Address correspondence to: Lei Kang or Yujun Dong, Department of Nuclear Medicine, Peking University First Hospital, No. 8 Xishiku Str., Xicheng Dist, Beijing, 100034, China. Phone: 86.10.83575252; Email: kanglei@bjmu.edu.cn (LK); dongy@hsc.pku.edu.cn (YD). Or to: Xiaojie Xu, Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing100071, China. Email: miraclexxj@126.com.
Authorship note: TG, ZC, BT, TW, and QY contributed equally to this work.
Find articles by Yang, Q. in: PubMed | Google Scholar
1Department of Nuclear Medicine and
2Department of Hematology, Peking University First Hospital, Beijing, China.
3Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing, China.
4Department of Pathology, Peking University First Hospital, Beijing, China.
Address correspondence to: Lei Kang or Yujun Dong, Department of Nuclear Medicine, Peking University First Hospital, No. 8 Xishiku Str., Xicheng Dist, Beijing, 100034, China. Phone: 86.10.83575252; Email: kanglei@bjmu.edu.cn (LK); dongy@hsc.pku.edu.cn (YD). Or to: Xiaojie Xu, Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing100071, China. Email: miraclexxj@126.com.
Authorship note: TG, ZC, BT, TW, and QY contributed equally to this work.
Find articles by Liu, H. in: PubMed | Google Scholar
1Department of Nuclear Medicine and
2Department of Hematology, Peking University First Hospital, Beijing, China.
3Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing, China.
4Department of Pathology, Peking University First Hospital, Beijing, China.
Address correspondence to: Lei Kang or Yujun Dong, Department of Nuclear Medicine, Peking University First Hospital, No. 8 Xishiku Str., Xicheng Dist, Beijing, 100034, China. Phone: 86.10.83575252; Email: kanglei@bjmu.edu.cn (LK); dongy@hsc.pku.edu.cn (YD). Or to: Xiaojie Xu, Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing100071, China. Email: miraclexxj@126.com.
Authorship note: TG, ZC, BT, TW, and QY contributed equally to this work.
Find articles by Liang, Z. in: PubMed | Google Scholar
1Department of Nuclear Medicine and
2Department of Hematology, Peking University First Hospital, Beijing, China.
3Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing, China.
4Department of Pathology, Peking University First Hospital, Beijing, China.
Address correspondence to: Lei Kang or Yujun Dong, Department of Nuclear Medicine, Peking University First Hospital, No. 8 Xishiku Str., Xicheng Dist, Beijing, 100034, China. Phone: 86.10.83575252; Email: kanglei@bjmu.edu.cn (LK); dongy@hsc.pku.edu.cn (YD). Or to: Xiaojie Xu, Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing100071, China. Email: miraclexxj@126.com.
Authorship note: TG, ZC, BT, TW, and QY contributed equally to this work.
Find articles by Wang, Q. in: PubMed | Google Scholar
1Department of Nuclear Medicine and
2Department of Hematology, Peking University First Hospital, Beijing, China.
3Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing, China.
4Department of Pathology, Peking University First Hospital, Beijing, China.
Address correspondence to: Lei Kang or Yujun Dong, Department of Nuclear Medicine, Peking University First Hospital, No. 8 Xishiku Str., Xicheng Dist, Beijing, 100034, China. Phone: 86.10.83575252; Email: kanglei@bjmu.edu.cn (LK); dongy@hsc.pku.edu.cn (YD). Or to: Xiaojie Xu, Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing100071, China. Email: miraclexxj@126.com.
Authorship note: TG, ZC, BT, TW, and QY contributed equally to this work.
Find articles by Zhang, Y. in: PubMed | Google Scholar
1Department of Nuclear Medicine and
2Department of Hematology, Peking University First Hospital, Beijing, China.
3Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing, China.
4Department of Pathology, Peking University First Hospital, Beijing, China.
Address correspondence to: Lei Kang or Yujun Dong, Department of Nuclear Medicine, Peking University First Hospital, No. 8 Xishiku Str., Xicheng Dist, Beijing, 100034, China. Phone: 86.10.83575252; Email: kanglei@bjmu.edu.cn (LK); dongy@hsc.pku.edu.cn (YD). Or to: Xiaojie Xu, Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing100071, China. Email: miraclexxj@126.com.
Authorship note: TG, ZC, BT, TW, and QY contributed equally to this work.
Find articles by Sun, Y. in: PubMed | Google Scholar
1Department of Nuclear Medicine and
2Department of Hematology, Peking University First Hospital, Beijing, China.
3Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing, China.
4Department of Pathology, Peking University First Hospital, Beijing, China.
Address correspondence to: Lei Kang or Yujun Dong, Department of Nuclear Medicine, Peking University First Hospital, No. 8 Xishiku Str., Xicheng Dist, Beijing, 100034, China. Phone: 86.10.83575252; Email: kanglei@bjmu.edu.cn (LK); dongy@hsc.pku.edu.cn (YD). Or to: Xiaojie Xu, Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing100071, China. Email: miraclexxj@126.com.
Authorship note: TG, ZC, BT, TW, and QY contributed equally to this work.
Find articles by Di, M. in: PubMed | Google Scholar
1Department of Nuclear Medicine and
2Department of Hematology, Peking University First Hospital, Beijing, China.
3Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing, China.
4Department of Pathology, Peking University First Hospital, Beijing, China.
Address correspondence to: Lei Kang or Yujun Dong, Department of Nuclear Medicine, Peking University First Hospital, No. 8 Xishiku Str., Xicheng Dist, Beijing, 100034, China. Phone: 86.10.83575252; Email: kanglei@bjmu.edu.cn (LK); dongy@hsc.pku.edu.cn (YD). Or to: Xiaojie Xu, Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing100071, China. Email: miraclexxj@126.com.
Authorship note: TG, ZC, BT, TW, and QY contributed equally to this work.
Find articles by Yuan, T. in: PubMed | Google Scholar
1Department of Nuclear Medicine and
2Department of Hematology, Peking University First Hospital, Beijing, China.
3Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing, China.
4Department of Pathology, Peking University First Hospital, Beijing, China.
Address correspondence to: Lei Kang or Yujun Dong, Department of Nuclear Medicine, Peking University First Hospital, No. 8 Xishiku Str., Xicheng Dist, Beijing, 100034, China. Phone: 86.10.83575252; Email: kanglei@bjmu.edu.cn (LK); dongy@hsc.pku.edu.cn (YD). Or to: Xiaojie Xu, Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing100071, China. Email: miraclexxj@126.com.
Authorship note: TG, ZC, BT, TW, and QY contributed equally to this work.
Find articles by Qiu, Y. in: PubMed | Google Scholar
1Department of Nuclear Medicine and
2Department of Hematology, Peking University First Hospital, Beijing, China.
3Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing, China.
4Department of Pathology, Peking University First Hospital, Beijing, China.
Address correspondence to: Lei Kang or Yujun Dong, Department of Nuclear Medicine, Peking University First Hospital, No. 8 Xishiku Str., Xicheng Dist, Beijing, 100034, China. Phone: 86.10.83575252; Email: kanglei@bjmu.edu.cn (LK); dongy@hsc.pku.edu.cn (YD). Or to: Xiaojie Xu, Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing100071, China. Email: miraclexxj@126.com.
Authorship note: TG, ZC, BT, TW, and QY contributed equally to this work.
Find articles by Du, Y. in: PubMed | Google Scholar
1Department of Nuclear Medicine and
2Department of Hematology, Peking University First Hospital, Beijing, China.
3Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing, China.
4Department of Pathology, Peking University First Hospital, Beijing, China.
Address correspondence to: Lei Kang or Yujun Dong, Department of Nuclear Medicine, Peking University First Hospital, No. 8 Xishiku Str., Xicheng Dist, Beijing, 100034, China. Phone: 86.10.83575252; Email: kanglei@bjmu.edu.cn (LK); dongy@hsc.pku.edu.cn (YD). Or to: Xiaojie Xu, Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing100071, China. Email: miraclexxj@126.com.
Authorship note: TG, ZC, BT, TW, and QY contributed equally to this work.
Find articles by Song, L. in: PubMed | Google Scholar
1Department of Nuclear Medicine and
2Department of Hematology, Peking University First Hospital, Beijing, China.
3Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing, China.
4Department of Pathology, Peking University First Hospital, Beijing, China.
Address correspondence to: Lei Kang or Yujun Dong, Department of Nuclear Medicine, Peking University First Hospital, No. 8 Xishiku Str., Xicheng Dist, Beijing, 100034, China. Phone: 86.10.83575252; Email: kanglei@bjmu.edu.cn (LK); dongy@hsc.pku.edu.cn (YD). Or to: Xiaojie Xu, Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing100071, China. Email: miraclexxj@126.com.
Authorship note: TG, ZC, BT, TW, and QY contributed equally to this work.
Find articles by Wu, S. in: PubMed | Google Scholar
1Department of Nuclear Medicine and
2Department of Hematology, Peking University First Hospital, Beijing, China.
3Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing, China.
4Department of Pathology, Peking University First Hospital, Beijing, China.
Address correspondence to: Lei Kang or Yujun Dong, Department of Nuclear Medicine, Peking University First Hospital, No. 8 Xishiku Str., Xicheng Dist, Beijing, 100034, China. Phone: 86.10.83575252; Email: kanglei@bjmu.edu.cn (LK); dongy@hsc.pku.edu.cn (YD). Or to: Xiaojie Xu, Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing100071, China. Email: miraclexxj@126.com.
Authorship note: TG, ZC, BT, TW, and QY contributed equally to this work.
Find articles by Wang, W. in: PubMed | Google Scholar
1Department of Nuclear Medicine and
2Department of Hematology, Peking University First Hospital, Beijing, China.
3Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing, China.
4Department of Pathology, Peking University First Hospital, Beijing, China.
Address correspondence to: Lei Kang or Yujun Dong, Department of Nuclear Medicine, Peking University First Hospital, No. 8 Xishiku Str., Xicheng Dist, Beijing, 100034, China. Phone: 86.10.83575252; Email: kanglei@bjmu.edu.cn (LK); dongy@hsc.pku.edu.cn (YD). Or to: Xiaojie Xu, Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing100071, China. Email: miraclexxj@126.com.
Authorship note: TG, ZC, BT, TW, and QY contributed equally to this work.
Find articles by Xu, X. in: PubMed | Google Scholar
1Department of Nuclear Medicine and
2Department of Hematology, Peking University First Hospital, Beijing, China.
3Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing, China.
4Department of Pathology, Peking University First Hospital, Beijing, China.
Address correspondence to: Lei Kang or Yujun Dong, Department of Nuclear Medicine, Peking University First Hospital, No. 8 Xishiku Str., Xicheng Dist, Beijing, 100034, China. Phone: 86.10.83575252; Email: kanglei@bjmu.edu.cn (LK); dongy@hsc.pku.edu.cn (YD). Or to: Xiaojie Xu, Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing100071, China. Email: miraclexxj@126.com.
Authorship note: TG, ZC, BT, TW, and QY contributed equally to this work.
Find articles by Dong, Y. in: PubMed | Google Scholar
1Department of Nuclear Medicine and
2Department of Hematology, Peking University First Hospital, Beijing, China.
3Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing, China.
4Department of Pathology, Peking University First Hospital, Beijing, China.
Address correspondence to: Lei Kang or Yujun Dong, Department of Nuclear Medicine, Peking University First Hospital, No. 8 Xishiku Str., Xicheng Dist, Beijing, 100034, China. Phone: 86.10.83575252; Email: kanglei@bjmu.edu.cn (LK); dongy@hsc.pku.edu.cn (YD). Or to: Xiaojie Xu, Department of Genetic Engineering, Beijing Institute of Biotechnology, Beijing100071, China. Email: miraclexxj@126.com.
Authorship note: TG, ZC, BT, TW, and QY contributed equally to this work.
Find articles by Kang, L. in: PubMed | Google Scholar
Published June 30, 2026 - More info
J Clin Invest. 2026;136(18):e207391. https://doi.org/10.1172/JCI207391.
© 2026 Gu et al. This work is licensed under the Creative Commons Attribution 4.0 International License. To view a copy of this license, visit http://creativecommons.org/licenses/by/4.0/.
Received: March 26, 2026; Accepted: June 11, 2026

Related article:
Abstract
Multiple myeloma is a systemic and spatially heterogeneous cancer of plasma cells. Available methods for diagnosing and monitoring disease do not fully capture its heterogeneity. For instance, bone marrow sampling is anatomically limited and [18F]FDG PET/CT reflects glucose metabolism rather than a specific target. In this issue of JCI, Gu et al. reported a prospective phase I study of [68Ga]Ga-PFBC01, a nanobody tracer targeting B cell maturation antigen (BCMA). The study presents a coherent translational pathway for [68Ga]Ga-PFBC01 PET and demonstrates high sensitivity, associations with tissue and circulating disease measures, and clinical management impact. By shifting myeloma imaging from metabolic assessment toward target biology, [68Ga]Ga-PFBC01 PET may visualize whole-body disease distribution and actionable target expression, while blood-pool activity may reflect systemic antigen biology (Figure 1).
Authors
Yangmeihui Song, Wenyu Song, Weibo Cai

-
Results
In vitro characterization.
Preclinical studies established the binding specificity, stability, and imaging performance of 68Ga-PFBC01. A BCMA-specific single-domain antibody (sdAb) library was generated through alpaca immunization followed by standard molecular cloning procedures, including RNA extraction, PCR amplification, ligation, and bacterial transformation (Figure 1A). SDS-PAGE confirmed successful purification of the sdAb, yielding a single protein band with purity exceeding 90% following Ni2+ affinity chromatography (Figure 1B). ELISA and biolayer interferometry confirmed high affinity and specificity toward recombinant BCMA (Figure 1, C and D). In vitro assays demonstrated selective uptake of 68Ga-PFBC01 in BCMA-positive H929 cells (1.58 ± 0.20 %IA/106 cells), significantly exceeding that in H929 blocking cells (0.80 ± 0.11 %IA/106 cells, P = 0.009) and BCMA-negative K562 cells (1.05 ± 0.13 %IA/106 cells, P = 0.024; Figure 1E). Flow cytometry further validated these findings, showing strong fluorescence shifts in BCMA-positive lines but not in K562 cells (Figure 1F). 68Ga-PFBC01 exhibited excellent radiochemical stability (> 98%) in PBS and FBS over 4 hours (Figure 1G and Supplemental Figure 1; supplemental material available online with this article; https://doi.org/10.1172/JCI207391DS1).
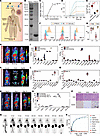 Figure 1
Preparation and preclinical characterization of 68Ga-PFBC01 for PET/CT imaging. (A) Schematic illustration of the 68Ga-PFBC01 PET/CT probe for the precise diagnosis of MM. (B) SDS-PAGE confirmed greater than 90% purity of the sdAb following Ni2+ affinity purification. (C) ELISA assay confirmed the high binding affinity of the PFBC01 for the BCMA protein. (D) Bio-layer interferometry showed strong binding affinity between PFBC01 and BCMA protein. (E) Cell uptake and blocking assays demonstrated specific binding in H929 cells compared with blocking and K562 cells (n = 3). (F) Flow cytometry analysis showing rightward fluorescence shift in BCMA-positive H929 and MM.1S cells. (G) TLC analysis showed high radiochemical purity in PBS and FBS (n = 3). (H) Maximum intensity projection (MIP) PET images of subcutaneous tumor models. (I) Quantitative Region of Interest (ROI) analysis of PET imaging in subcutaneous tumor models (n = 4 for H929; n = 7 for H929 blocking; n = 4 for K562). (J) Biodistribution study at 1 hour after injection corroborating the PET findings of subcutaneous tumor models. (K) Representative PET images (coronal, axial, and sagittal views) of an orthotopic MM.1S model. The probe efficiently accumulated in various tumor foci (white arrows), clearly delineating even small lesions. (L) Quantitative PET analysis of the orthotopic model (n = 3). (M) Biodistribution analysis at 1 hour after injection of the orthotopic model (n = 3). (N) MIP PET images for monitoring therapy response (DVD regimen). A reduction in tumor uptake was evident on day 5 after treatment, with a further decrease observed on day 10. (O) Quantitative PET analysis of therapy response (n = 3). (P) Histopathology and IHC confirmed strong BCMA expressions in H929 and MM.1S tumors, but minimal staining in K562 tumors. (Q) Dynamic PET imaging following intravenous injection of the probe in a healthy cynomolgus monkey. (R) Quantitative PET analysis in healthy cynomolgus monkeys showed rapid clearance and predominant renal excretion of the tracer (n = 3).
In vivo imaging and biodistribution.
In subcutaneous xenograft models, 68Ga-PFBC01 PET/CT showed intense uptake in BCMA-positive H929 tumors but minimal signal in blocking and BCMA-negative controls (Figure 1H). Quantitative region-of-interest (ROI) analysis showed tumor uptake of 3.21 ± 0.18 % percentage of injected dose per gram of tissue) (ID/g) in H929 mice, significantly higher than in H929-blocking (1.60 ± 0.38 %ID/g) and K562 (0.70 ± 0.24 %ID/g) groups (Figure 1I). Ex vivo biodistribution at 1 hour after injection corroborated the PET findings (4.00 ± 1.55 %ID/g in the H929 model versus 1.12 ± 0.24 %ID/g in the H929-blocking group, P = 0.033; Figure 1J). In orthotopic MM.1S models, 68Ga-PFBC01 PET/CT clearly demonstrated multifocal skeletal lesions (Figure 1K), ranging from 1.33 ± 0.11 to 1.61 ± 0.09 %ID/g across skeletal sites (Figure 1L), consistent with ex vivo measurements (Figure 1M).
To assess treatment monitoring capability, 68Ga-PFBC01 PET was used to evaluate response to the DVD (daratumumab, bortezomib, and dexamethasone) chemotherapy (16). Tumor uptake markedly declined by day 5 and further by day 10 from 3.93 ± 0.47 to 0.63 ± 0.00 %ID/g; Figure 1, N and O). IHC staining confirmed high BCMA expression in H929 and MM.1S tumors (Figure 1P).
In healthy cynomolgus monkeys, dynamic PET revealed rapid blood clearance (peak SUVmax = 13.7 ± 1.2 at 35 s) and renal excretion, with predominant uptake in kidneys (peak SUVmax = 36–41 at 3,600 s; Figure 1, Q and R). Based on dynamic PET imaging in healthy cynomolgus monkeys, preliminary dosimetry estimates of 68Ga-PFBC01 were calculated using the OLINDA/EXM software package (Version 2.2; Vanderbilt University, Nashville, Tennessee, USA), and the results are summarized in Supplemental Table 1.
Clinical investigation of 68Ga-PFBC01 PET/CT.
Between April 21, 2025, and September 4, 2025, a total of 52 eligible patients were screened for participation in this single-center, single-arm Phase I trial (Figure 2). Among them, 2 individuals withdrew consent prior to imaging. Consequently, 50 patients underwent 68Ga-PFBC01 PET/CT. Of these, 40 patients also underwent 18F-FDG PET/CT within a 2-week window before or after the 68Ga-PFBC01 scan, allowing for direct comparison between the 2 imaging modalities (Supplemental Table 2). All 50 patients had histopathological confirmation of multiple myeloma, ensuring diagnostic accuracy for subsequent analyses. Baseline characteristics are summarized in Supplemental Table 3.
Pathological Correlation of 68Ga-PFBC01 PET/CT.
To minimize observer bias, a deep learning–based algorithm was used to automatically segment skeletal structures on CT into thoracic, spinal, and pelvic regions and calculated regional SUVmean values to derive the overall burden (Supplemental Figure 2). Uptake of 68Ga-PFBC01 PET/CT showed a strong correlation with BCMA immunohistochemical expression, suggesting the binding specificity of 68Ga-PFBC01 to BCMA. Signal intensity increased progressively from BCMA IHC+ (Figure 3A) to BCMA IHC++ (Figure 3B) and BCMA IHC+++ (Figure 3C) in newly diagnosed patients with MM, a finding that was further confirmed quantitatively (Figure 3D). In addition to BCMA IHC, tracer uptake also correlated significantly with Vs38c (Figure 3E) and CD138 (Figure 3F) staining, supporting the concordance between molecular imaging and histopathologic plasma cell markers.
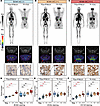 Figure 3
Pathological Correlation of 68Ga-PFBC01 PET/CT and 18F-FDG PET/CT with BCMA Expression in newly diagnosed patients with MM. (A) Head-to-head comparison of 68Ga-PFBC01 PET/CT and 18F-FDG in a patient with weak BCMA expression (+). (B) Head-to-head comparison of 68Ga-PFBC01 PET/CT and 18F-FDG in a patient with moderate BCMA expression (++). (C) Head-to-head comparison of 68Ga-PFBC01 PET/CT and 18F-FDG in a patient with strong BCMA expression (+++). (D) Head-to-head comparison of 68Ga-PFBC01 PET/CT and 18F-FDG in BCMA immunohistochemical staining. (E) Head-to-head comparison of 68Ga-PFBC01 PET/CT and 18F-FDG in Vs38c immunohistochemical staining. (F) Head-to-head comparison of 68Ga-PFBC01 PET/CT and 18F-FDG in CD138 immunohistochemical staining.
Diagnostic performance of 68Ga-PFBC01 PET/CT.
In diagnostic assessment, 68Ga-PFBC01 PET/CT clearly differentiated among control, smoldering multiple myeloma (sMM), MM, and plasma cell leukemia (PCL, Figure 4A). High lesion-to-background contrast was observed in the thoracic bones (Figure 4B), spine (Figure 4C), and pelvis (Figure 4D) — regions most frequently involved in MM — allowing site-specific disease detection in cases where 18F-FDG PET/CT failed to distinguish pathological from normal uptake. When integrated on a whole-body basis, 68Ga-PFBC01 PET/CT achieved more accurate stratification across the spectrum of plasma cell disorders, whereas 18F-FDG PET/CT was only able to distinguish controls from MM without discriminating intermediate states such as sMM or PCL (Figure 4E).
 Figure 4
Head-to-head comparison of 68Ga-PFBC01 and 18F-FDG PET/CT for the diagnosis of plasma cell disorders. (A) Representative 68Ga-PFBC01 and 18F-FDG PET/CT images in patients with different stages of plasma cell disorders. From left to right: healthy control, smoldering multiple myeloma (SMM), multiple myeloma (MM), and plasma cell leukemia (PCL). (B) Quantitative comparison of thorax burden between 68Ga-PFBC01 and 18F-FDG PET/CT. (C) Quantitative comparison of spine burden between 68Ga-PFBC01 and 18F-FDG PET/CT. (D) Quantitative comparison of pelvis burden between 68Ga-PFBC01 and 18F-FDG PET/CT. (E) Quantitative comparison of overall burden between 68Ga-PFBC01 and 18F-FDG PET/CT.
Clinical decision-making guided by 68Ga-PFBC01 PET/CT.
68Ga-PFBC01 PET/CT demonstrated clear clinical utility in guiding therapeutic decisions. In the first representative case, a patient with sMM showed intense 68Ga-PFBC01 uptake, leading to treatment escalation from active monitoring (initially determined based on 18F-FDG PET/CT and clinical history) to the addition of first-line therapy (Figure 5A). In contrast, another patient with treated MM exhibited residual glucose metabolism on 18F-FDG PET/CT and was initially planned to continue maintenance therapy. However, 68Ga-PFBC01 PET/CT revealed no significant residual lesions, prompting treatment deescalation to active monitoring, which was later supported by MRD negativity (Figure 5B). A comprehensive treatment-flow Sankey diagram (Figure 5C) further illustrates the impact of 68Ga-PFBC01 on clinical decision making. Among patients with solitary plasmacytoma (n = 2), 18F-FDG PET/CT suggested continuation of the current regimen after surgical resection, whereas persistent BCMA-targeted uptake on 68Ga-PFBC01 prompted escalation to add first-line radiotherapy. Two patients with sMM transitioned from active monitoring to first-line therapy based on strong 68Ga-PFBC01 uptake. Two patients with extramedullary disease (EMD) escalated from first-line to second-line therapy due to specific 68Ga-PFBC01 avid lesions. One newly diagnosed patient with MM similarly escalated from active monitoring to first-line therapy. Conversely, 4 posttreatment patients with MM who exhibited residual 18F-FDG uptake but no detectable 68Ga-PFBC01 lesions underwent therapy deescalation from maintenance to active monitoring. Additionally, 1 treated patient with MM who achieved strict complete response (sCR) showed no 68Ga-PFBC01 uptake, supporting treatment discontinuation.
 Figure 5
Head-to-head comparison of 68Ga-PFBC01 and 18F-FDG PET/CT for therapy guidance and response assessment in multiple myeloma. (A) Representative PET/CT images of patients who underwent therapy escalation based on 68Ga-PFBC01 findings. (B) Representative PET/CT images of patients who underwent therapy deescalation based on 68Ga-PFBC01 findings. (C) Summary of therapy decisions guided by 68Ga-PFBC01. (D) Comparison between serological response according to the International Myeloma Working Group (IMWG) criteria and PET/CT response assessed by 68Ga-PFBC01. (E) Comparison between serological IMWG response and PET/CT response assessed by 18F-FDG. (F) Representative 68Ga-PFBC01 and 18F-FDG PET/CT images acquired after treatment in patients with multiple myeloma, from left to right: patient achieved partial response (PR) and patient achieved complete response (CR). (G) Quantitative comparison of thorax burden between 68Ga-PFBC01 and 18F-FDG PET/CT during treatment evaluation. (H) Quantitative comparison of spine burden between 68Ga-PFBC01 and 18F-FDG PET/CT during treatment evaluation. (I) Quantitative comparison of pelvis burden between 68Ga-PFBC01 and 18F-FDG PET/CT during treatment evaluation. (J) Quantitative comparison of overall burden between 68Ga-PFBC01 and 18F-FDG PET/CT during treatment evaluation.
Treatment response evaluation in 68Ga-PFBC01 PET/CT.
Further comparison of PET-based response evaluation according to IMWG criteria revealed strong concordance between 68Ga-PFBC01 PET/CT and clinical outcomes. Among 8 patients with VGPR or PR, all were categorized as PR, while 17 patients with sCR or CR were classified as CR (n = 11) or PR (n = 6) on 68Ga-PFBC01 PET/CT (Figure 5D). In contrast, 18F-FDG PET/CT demonstrated lower discriminative accuracy: among 5 patients with VGPR or PR, 3 were rated as partial metabolic response (PMR) and 2 as complete metabolic response (CMR); among 10 patients with sCR or CR, only 4 were categorized as CMR and 6 as PMR (Figure 5E).
For response visualization, 68Ga-PFBC01 PET/CT clearly differentiated disease states at PR, and CR (Figure 5F). High lesion-to-background contrast was consistently preserved across thoracic bones (Figure 5G), spine (Figure 5H), and pelvis (Figure 5I). In contrast, 18F-FDG PET/CT, reflecting glucose metabolism, often displayed nonspecific posttreatment uptake, reducing its ability to distinguish response phases regionally or in overall burden assessment. In whole-body analyses, 68Ga-PFBC01 PET/CT showed superior sensitivity and specificity for discriminating remission states compared with 18F-FDG PET/CT, which frequently overestimated metabolic activity in posttherapy lesions (Figure 5J).
Tumor burden and prognostic evaluation in 68Ga-PFBC01 PET/CT.
Quantitative analysis further revealed that 68Ga-PFBC01 PET/CT provided an accurate reflection of tumor burden. The total PET intensity correlated positively with M protein level (R = 0.325, P = 0.026, Figure 6A), free κ light chain (R = 0.340, P = 0.015, Figure 6B), free λ light chain (R = 0.437, P = 0.001, Figure 6C), soluble BCMA (R = 0.433, P = 0.050, Figure 6D), bone marrow plasma cell percentage (R = 0.682, P < 0.001, Figure 6E), and metabolic tumor volume (R = 0.343, P = 0.012, Figure 6F). Tracer uptake also stratified prognostic subgroups, distinguishing International Scoring System (ISS) stage III from stages I (P = 0.004) and II (P = 0.006, Figure 6G), Durie–Salmon (DS) stage III A from III B (P = 0.006, Figure 6H), and standard from high-risk cytogenetic profiles (P < 0.001, Figure 6I). These findings indicate that 68Ga-PFBC01 PET/CT captures disease biology reflected in both tumor burden and prognosis.
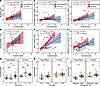 Figure 6
Head-to-head comparison of 68Ga-PFBC01 and 18F-FDG PET/CT for tumor burden evaluation and prognostic assessment in multiple myeloma. (A) Correlation between PET/CT–derived overall burden and M protein (g/L). (B) Correlation between PET/CT–derived overall burden and free κ chain (mg/dL). (C) Correlation between PET/CT–derived overall burden and free λ chain (mg/dL). (D) Correlation of 68Ga-PFBC01 and 18F-FDG PET/CT–derived overall burden with serum soluble BCMA levels. (E) Correlation between PET/CT–derived overall burden and bone marrow plasma cell percentage. (F) Correlation between PET/CT–derived overall burden and metabolic tumor volume (MTV). (G) Prognostic evaluation based on International Staging System (ISS) stage. (H) Prognostic evaluation based on Durie–Salmon (DS) stage. (I) Prognostic evaluation according to cytogenetic risk.
Diagnostic accuracy and interreader consistency of 68Ga-PFBC01.
In head-to-head regional comparisons across 9 anatomic compartments — skull, scapula, humerus, sternum, ribs, spine, pelvis, femur, and EMD — 68Ga-PFBC01 PET/CT consistently outperformed 18F-FDG PET/CT (Figure 7A). On a per-patient basis, sensitivity [96.9% (83.8%–99.9%) versus 84.6% (65.1%–95.6%)], specificity [71.4% (47.8%–88.7%) versus 60.0% (32.3%–83.7%)], positive predictive value (PPV) [83.8% (68.0%–93.8%) versus 78.6% (59.0%–91.7%)], and negative predictive value (NPV) [93.8% (69.8%–99.8%) versus 69.2% (38.6–%90.9%)] were all higher for 68Ga-PFBC01 PET/CT (Figure 7B). Interreader agreement analysis using Fleiss’ κ showed improved consistency for 68Ga-PFBC01 PET/CT across both whole-body diagnosis and site-specific evaluations compared with 18F-FDG PET/CT (Figure 7C).
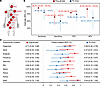 Figure 7
Evaluation of diagnostic performance between 68Ga-PFBC01 and 18F-FDG PET/CT. (A) Schematic diagram of anatomical regions evaluated for image interpretation, including the skull, scapula, humerus, sternum, rib, spine, pelvis, femur, and extramedullary disease (EMD). (B) Head-to-head comparison of diagnostic performance between 68Ga-PFBC01 and 18F-FDG PET/CT, from left to right: sensitivity, specificity, positive predictive value (PPV), and negative predictive value (NPV). (C) Comparison of interreader consistency between 68Ga-PFBC01 and 18F-FDG PET/CT across diagnostic categories and anatomical sites.
Blood-pool signal as a biomarker of systemic disease activity.
An unexpected yet biologically meaningful finding was the high blood-pool uptake of 68Ga-PFBC01 PET/CT, distinct from the rapid clearance typically observed with nanobody-based tracers (17). Automated segmentation and quantification of blood-pool SUVmean (Supplemental Figure 3A) were calculated. Blood-pool SUVmean increased progressively with disease severity (Supplemental Figure 3B), demonstrating strong association with treatment response categories (Supplemental Figure 3C). Moreover, blood-pool activity correlated with prognostic indices, including ISS stage (Supplemental Figure 3D), DS stage (Supplemental Figure 3E), and cytogenetic risk classification (Supplemental Figure 3F), as well as with overall disease burden (R = 0.736, P < 0.001; Supplemental Figure 3G), bone marrow plasma cell percentage (R = 0.545, P < 0.001; Supplemental Figure 3H), and CD138 staining (Supplemental Figure 3I). Plasma-soluble BCMA levels were measured by indirect ELISA (Supplemental Figure 3J) and correlated positively with blood pool SUVmean (R = 0.899, P < 0.001; Supplemental Figure 3K). These results suggest that blood-pool activity may serve as a surrogate imaging biomarker for circulating BCMA load, providing an integrated assessment of systemic disease activity.
Safety evaluation of 68Ga-PFBC01 PET/CT.
In 2 (4%) of 50 participants, 2 adverse events were classified as possibly related to 68Ga-PFBC01 PET/CT within 30 days (Supplemental Table 4), including nausea (n = 1) and dizziness (n = 1).


Copyright © 2026 American Society for Clinical Investigation
ISSN: 0021-9738 (print), 1558-8238 (online)