
Advertisement
Research ArticleHematologyImmunology
Open Access |  10.1172/JCI202932
Ex vivo pretreatment with venetoclax boosts antileukemic efficacy of therapeutic γδ T cells in AML models
Xingchi Chen,1,2,3 Lin Zhang,4 Bingbing Yan,1,2,3 Yinqiang Sui,5 Weiwei Ma,5 Hui Zhao,5 Yining Wang,1,2,3 Kepeng Yang,1,2,3 Jiewen Ma,1,2,3 Baolin Tang,1,2,3 Yonghui Zhang,4 and Xiaoyu Zhu1,2,3
1Department of Hematology, Centre for Leading Medicine and Advanced Technologies of IHM, the First Affiliated Hospital of USTC, Division of Life Sciences and Medicine, and
2Blood and Cell Therapy Institute, Division of Life Sciences and Medicine, University of Science and Technology of China (USTC), Hefei, China.
3Anhui Provincial Key Laboratory of Blood Research and Applications, Hefei, China.
4Tsinghua-Peking Center for Life Sciences, School of Pharmaceutical Sciences, Tsinghua University, Beijing, China.
5UnicetBio Co., Ltd., Beijing, China.
Address correspondence to: Xiaoyu Zhu, No. 17 Lujiang Road, Luyang District, Hefei, Anhui 230001, China. Phone: 86.0551.62283347; Email: xiaoyuz@ustc.edu.cn. Or to: Yonghui Zhang, Tsinghua University, Beijing 100084, China. Phone: 86.010.62797881; Email: zhangyonghui@tsinghua.edu.cn.
Find articles by Chen, X. in: PubMed | Google Scholar
1Department of Hematology, Centre for Leading Medicine and Advanced Technologies of IHM, the First Affiliated Hospital of USTC, Division of Life Sciences and Medicine, and
2Blood and Cell Therapy Institute, Division of Life Sciences and Medicine, University of Science and Technology of China (USTC), Hefei, China.
3Anhui Provincial Key Laboratory of Blood Research and Applications, Hefei, China.
4Tsinghua-Peking Center for Life Sciences, School of Pharmaceutical Sciences, Tsinghua University, Beijing, China.
5UnicetBio Co., Ltd., Beijing, China.
Address correspondence to: Xiaoyu Zhu, No. 17 Lujiang Road, Luyang District, Hefei, Anhui 230001, China. Phone: 86.0551.62283347; Email: xiaoyuz@ustc.edu.cn. Or to: Yonghui Zhang, Tsinghua University, Beijing 100084, China. Phone: 86.010.62797881; Email: zhangyonghui@tsinghua.edu.cn.
Find articles by Zhang, L. in: PubMed | Google Scholar
1Department of Hematology, Centre for Leading Medicine and Advanced Technologies of IHM, the First Affiliated Hospital of USTC, Division of Life Sciences and Medicine, and
2Blood and Cell Therapy Institute, Division of Life Sciences and Medicine, University of Science and Technology of China (USTC), Hefei, China.
3Anhui Provincial Key Laboratory of Blood Research and Applications, Hefei, China.
4Tsinghua-Peking Center for Life Sciences, School of Pharmaceutical Sciences, Tsinghua University, Beijing, China.
5UnicetBio Co., Ltd., Beijing, China.
Address correspondence to: Xiaoyu Zhu, No. 17 Lujiang Road, Luyang District, Hefei, Anhui 230001, China. Phone: 86.0551.62283347; Email: xiaoyuz@ustc.edu.cn. Or to: Yonghui Zhang, Tsinghua University, Beijing 100084, China. Phone: 86.010.62797881; Email: zhangyonghui@tsinghua.edu.cn.
Find articles by Yan, B. in: PubMed | Google Scholar
1Department of Hematology, Centre for Leading Medicine and Advanced Technologies of IHM, the First Affiliated Hospital of USTC, Division of Life Sciences and Medicine, and
2Blood and Cell Therapy Institute, Division of Life Sciences and Medicine, University of Science and Technology of China (USTC), Hefei, China.
3Anhui Provincial Key Laboratory of Blood Research and Applications, Hefei, China.
4Tsinghua-Peking Center for Life Sciences, School of Pharmaceutical Sciences, Tsinghua University, Beijing, China.
5UnicetBio Co., Ltd., Beijing, China.
Address correspondence to: Xiaoyu Zhu, No. 17 Lujiang Road, Luyang District, Hefei, Anhui 230001, China. Phone: 86.0551.62283347; Email: xiaoyuz@ustc.edu.cn. Or to: Yonghui Zhang, Tsinghua University, Beijing 100084, China. Phone: 86.010.62797881; Email: zhangyonghui@tsinghua.edu.cn.
Find articles by Sui, Y. in: PubMed | Google Scholar
1Department of Hematology, Centre for Leading Medicine and Advanced Technologies of IHM, the First Affiliated Hospital of USTC, Division of Life Sciences and Medicine, and
2Blood and Cell Therapy Institute, Division of Life Sciences and Medicine, University of Science and Technology of China (USTC), Hefei, China.
3Anhui Provincial Key Laboratory of Blood Research and Applications, Hefei, China.
4Tsinghua-Peking Center for Life Sciences, School of Pharmaceutical Sciences, Tsinghua University, Beijing, China.
5UnicetBio Co., Ltd., Beijing, China.
Address correspondence to: Xiaoyu Zhu, No. 17 Lujiang Road, Luyang District, Hefei, Anhui 230001, China. Phone: 86.0551.62283347; Email: xiaoyuz@ustc.edu.cn. Or to: Yonghui Zhang, Tsinghua University, Beijing 100084, China. Phone: 86.010.62797881; Email: zhangyonghui@tsinghua.edu.cn.
Find articles by Ma, W. in: PubMed | Google Scholar
1Department of Hematology, Centre for Leading Medicine and Advanced Technologies of IHM, the First Affiliated Hospital of USTC, Division of Life Sciences and Medicine, and
2Blood and Cell Therapy Institute, Division of Life Sciences and Medicine, University of Science and Technology of China (USTC), Hefei, China.
3Anhui Provincial Key Laboratory of Blood Research and Applications, Hefei, China.
4Tsinghua-Peking Center for Life Sciences, School of Pharmaceutical Sciences, Tsinghua University, Beijing, China.
5UnicetBio Co., Ltd., Beijing, China.
Address correspondence to: Xiaoyu Zhu, No. 17 Lujiang Road, Luyang District, Hefei, Anhui 230001, China. Phone: 86.0551.62283347; Email: xiaoyuz@ustc.edu.cn. Or to: Yonghui Zhang, Tsinghua University, Beijing 100084, China. Phone: 86.010.62797881; Email: zhangyonghui@tsinghua.edu.cn.
Find articles by Zhao, H. in: PubMed | Google Scholar
1Department of Hematology, Centre for Leading Medicine and Advanced Technologies of IHM, the First Affiliated Hospital of USTC, Division of Life Sciences and Medicine, and
2Blood and Cell Therapy Institute, Division of Life Sciences and Medicine, University of Science and Technology of China (USTC), Hefei, China.
3Anhui Provincial Key Laboratory of Blood Research and Applications, Hefei, China.
4Tsinghua-Peking Center for Life Sciences, School of Pharmaceutical Sciences, Tsinghua University, Beijing, China.
5UnicetBio Co., Ltd., Beijing, China.
Address correspondence to: Xiaoyu Zhu, No. 17 Lujiang Road, Luyang District, Hefei, Anhui 230001, China. Phone: 86.0551.62283347; Email: xiaoyuz@ustc.edu.cn. Or to: Yonghui Zhang, Tsinghua University, Beijing 100084, China. Phone: 86.010.62797881; Email: zhangyonghui@tsinghua.edu.cn.
Find articles by Wang, Y. in: PubMed | Google Scholar
1Department of Hematology, Centre for Leading Medicine and Advanced Technologies of IHM, the First Affiliated Hospital of USTC, Division of Life Sciences and Medicine, and
2Blood and Cell Therapy Institute, Division of Life Sciences and Medicine, University of Science and Technology of China (USTC), Hefei, China.
3Anhui Provincial Key Laboratory of Blood Research and Applications, Hefei, China.
4Tsinghua-Peking Center for Life Sciences, School of Pharmaceutical Sciences, Tsinghua University, Beijing, China.
5UnicetBio Co., Ltd., Beijing, China.
Address correspondence to: Xiaoyu Zhu, No. 17 Lujiang Road, Luyang District, Hefei, Anhui 230001, China. Phone: 86.0551.62283347; Email: xiaoyuz@ustc.edu.cn. Or to: Yonghui Zhang, Tsinghua University, Beijing 100084, China. Phone: 86.010.62797881; Email: zhangyonghui@tsinghua.edu.cn.
Find articles by Yang, K. in: PubMed | Google Scholar
1Department of Hematology, Centre for Leading Medicine and Advanced Technologies of IHM, the First Affiliated Hospital of USTC, Division of Life Sciences and Medicine, and
2Blood and Cell Therapy Institute, Division of Life Sciences and Medicine, University of Science and Technology of China (USTC), Hefei, China.
3Anhui Provincial Key Laboratory of Blood Research and Applications, Hefei, China.
4Tsinghua-Peking Center for Life Sciences, School of Pharmaceutical Sciences, Tsinghua University, Beijing, China.
5UnicetBio Co., Ltd., Beijing, China.
Address correspondence to: Xiaoyu Zhu, No. 17 Lujiang Road, Luyang District, Hefei, Anhui 230001, China. Phone: 86.0551.62283347; Email: xiaoyuz@ustc.edu.cn. Or to: Yonghui Zhang, Tsinghua University, Beijing 100084, China. Phone: 86.010.62797881; Email: zhangyonghui@tsinghua.edu.cn.
Find articles by Ma, J. in: PubMed | Google Scholar
1Department of Hematology, Centre for Leading Medicine and Advanced Technologies of IHM, the First Affiliated Hospital of USTC, Division of Life Sciences and Medicine, and
2Blood and Cell Therapy Institute, Division of Life Sciences and Medicine, University of Science and Technology of China (USTC), Hefei, China.
3Anhui Provincial Key Laboratory of Blood Research and Applications, Hefei, China.
4Tsinghua-Peking Center for Life Sciences, School of Pharmaceutical Sciences, Tsinghua University, Beijing, China.
5UnicetBio Co., Ltd., Beijing, China.
Address correspondence to: Xiaoyu Zhu, No. 17 Lujiang Road, Luyang District, Hefei, Anhui 230001, China. Phone: 86.0551.62283347; Email: xiaoyuz@ustc.edu.cn. Or to: Yonghui Zhang, Tsinghua University, Beijing 100084, China. Phone: 86.010.62797881; Email: zhangyonghui@tsinghua.edu.cn.
Find articles by Tang, B. in: PubMed | Google Scholar
1Department of Hematology, Centre for Leading Medicine and Advanced Technologies of IHM, the First Affiliated Hospital of USTC, Division of Life Sciences and Medicine, and
2Blood and Cell Therapy Institute, Division of Life Sciences and Medicine, University of Science and Technology of China (USTC), Hefei, China.
3Anhui Provincial Key Laboratory of Blood Research and Applications, Hefei, China.
4Tsinghua-Peking Center for Life Sciences, School of Pharmaceutical Sciences, Tsinghua University, Beijing, China.
5UnicetBio Co., Ltd., Beijing, China.
Address correspondence to: Xiaoyu Zhu, No. 17 Lujiang Road, Luyang District, Hefei, Anhui 230001, China. Phone: 86.0551.62283347; Email: xiaoyuz@ustc.edu.cn. Or to: Yonghui Zhang, Tsinghua University, Beijing 100084, China. Phone: 86.010.62797881; Email: zhangyonghui@tsinghua.edu.cn.
Find articles by Zhang, Y. in: PubMed | Google Scholar
1Department of Hematology, Centre for Leading Medicine and Advanced Technologies of IHM, the First Affiliated Hospital of USTC, Division of Life Sciences and Medicine, and
2Blood and Cell Therapy Institute, Division of Life Sciences and Medicine, University of Science and Technology of China (USTC), Hefei, China.
3Anhui Provincial Key Laboratory of Blood Research and Applications, Hefei, China.
4Tsinghua-Peking Center for Life Sciences, School of Pharmaceutical Sciences, Tsinghua University, Beijing, China.
5UnicetBio Co., Ltd., Beijing, China.
Address correspondence to: Xiaoyu Zhu, No. 17 Lujiang Road, Luyang District, Hefei, Anhui 230001, China. Phone: 86.0551.62283347; Email: xiaoyuz@ustc.edu.cn. Or to: Yonghui Zhang, Tsinghua University, Beijing 100084, China. Phone: 86.010.62797881; Email: zhangyonghui@tsinghua.edu.cn.
Find articles by
Zhu, X.
in:
PubMed
|
Google Scholar
|

Published July 23, 2026 - More info
J Clin Invest. 2026;136(18):e202932. https://doi.org/10.1172/JCI202932.
© 2026 Chen et al. This work is licensed under the Creative Commons Attribution 4.0 International License. To view a copy of this license, visit http://creativecommons.org/licenses/by/4.0/.
Received: November 26, 2025; Accepted: July 20, 2026


-
Results
Reanalysis of clinical scRNA-seq data reveals γδ T cell deficiency in relapsed patients with AML. The genesis of our present study was a reanalysis of a publicly available scRNA-seq dataset from Mathioudaki et al. (19) that examined a cohort of patients with AML who received an allogeneic hematopoietic stem cell transplantation (allo-HSCT) therapy. Among other analyses, the original study evaluated the cohort by splitting patients into those who achieved complete remission (CR) versus those who experienced relapse, and a striking finding was their discovery that the frequencies of both αβ T cells (CD8+) and γδ T cells (TRDC+, TRGC1+) were markedly higher in the CR patient group compared with the relapsed patients. This association between higher posttransplant γδ T cell abundance and improved clinical outcomes has also been reported in earlier allo-HSCT cohorts (20–24).
Our previous studies have examined the basic biology of γδ T cells (25–27). In light of this interest, we harnessed the scRNA-seq dataset for a focused analysis that extended beyond the scope of the original Mathioudaki et al. study. γδ T cells are circulating immune cells that undergo an activation process through which they sense and respond to “danger signals” indicating infection, stress, or cancer, notably doing so in an MHC-independent manner, thus distinguishing them from αβ T cells, which require antigens to be presented by MHC molecules (14). Once activated, γδ T cells quickly proliferate, produce inflammatory cytokines, and develop a potent cytotoxic response to kill a target cell (14).
Our focused reanalysis examined a total of 294 γδ T cells, with an average of 1,355 high-confidence genes per cell. Regarding specific genes, the γδ T cells of patients with relapsed AML showed markedly reduced expression levels for cytotoxic and activation-associated genes, including granzyme B (GZMB), CD69, TNF, and CXCR4. Conversely, the level of the senescence marker killer cell lectin like receptor subfamily G member 1 (KLRG1) was substantially higher in the γδ T cells of the relapsed patient group (Supplemental Table 1; supplemental material available online with this article; https://doi.org/10.1172/JCI202932DS1). These signals collectively support that the γδ T cells of the relapsed AML patient group exhibit impaired immune effector function (Figure 1A).
 Figure 1
Reanalysis of clinical scRNA-seq data reveals functional impairment and metabolic dysregulation of BM γδ T cells in relapsed AML after allo-HSCT. (A) Volcano plot of differentially expressed genes in BM γδ T cells from relapsed AML patients compared with those in CR after HSCT. Red and blue dots indicate significantly upregulated and downregulated genes, respectively (P < 0.05, log2FC > 0.25 or < –0.25). FC, fold-change. (B) Representative Gene Ontology (GO) terms and Kyoto Encyclopedia of Genes and Genomes (KEGG) pathways enriched among genes downregulated in relapsed AML.
Gene Ontology (GO) and Kyoto Encyclopedia of Genes and Genomes (KEGG) enrichment analysis indicated potentially informative changes in terms related to metabolism: the relapsed patient γδ T cells showed reductions for the terms fatty-acid catabolic process, fatty acid beta-oxidation, and sphingolipid signaling pathway. There were also a large variety of terms related to mitochondria identified in the GO analysis (e.g., mitochondrion, mitochondrial respirasome assembly, etc.) (Figure 1B and Supplemental Tables 2 and 3). Thus, patients with relapsed AML have a reduced overall number of γδ T cells compared with patients who achieve CR, and the γδ T cells of the relapsed patients have transcriptomes consistent with impaired immune effector function and dysregulation of metabolism and mitochondria.
An ex vivo pretreatment with venetoclax boosts the cytotoxic capacity of γδ T cells against AML. Given the better clinical outcomes of the CR versus relapsed AML patients, and considering the reduced numbers and apparently impaired functions of γδ T cells in patients with relapsed AML, we inferred that γδ T cells may somehow promote an antileukemic effect (22, 24, 28–30). A variety of recent studies have explored use of an ex vivo pretreatment for therapeutic T cells using the BCL-2 inhibitor venetoclax. These studies have collectively reported that the venetoclax pretreatment boosted the antileukemic efficacy for αβ T cells (8, 31) and CAR T cells (9) and have reported specific phenotypes for venetoclax-pretreated αβ T cells, including improvements in expansion, immune activation, and cytotoxic capacity, as well as memory-like phenotypes. Here, pursuing the potential of therapeutic γδ T cells for treating AML, we tested whether ex vivo exposure of γδ T cells to venetoclax confers similar beneficial outcomes as reported for αβ T cells, starting with boosted cytotoxic capacity.
Working with γδ T cells from healthy donors that we expanded with a standard protocol (32), we initially conducted a cytotoxicity assay to test killing activity against an AML cell line (KG-1α cells). We used an ex vivo venetoclax pretreatment (1 μM) of γδ T cells for 18 hours prior to the cytotoxicity assay (Figure 2A). Compared with the control (DMSO pretreatment) cells, our “ven-γδ T cells” showed a significantly increased extent of KG-1α cell killing (Figure 2B), a finding lending support to our speculation about potentially boosted therapeutic efficacy upon pretreatment of γδ T cells with venetoclax.
 Figure 2
Venetoclax enhances the antileukemic activity of γδ T cells. (A) Schematic workflow for screening compounds that enhance γδ T cell function. (B) Killing efficiency of venetoclax-pretreated γδ T cells (ven-γδ T cells) against KG-1α cells. γδ T cells from 7 healthy donors were pretreated with dimethyl sulfoxide (DMSO) or 1 μM venetoclax for 18 hours and cocultured with KG-1α cells at a 1:1 effector-to-target (E:T) ratio for 14–18 hours. Cytotoxicity was determined by luminescence. Each paired symbol represents 1 donor (n = 7). (C) Dose-dependent killing efficiency of ven-γδ T cells against MV4-11 and OCI-AML3 cells at a 1:1 E:T ratio (n = 3 biological replicates). Data represent mean ± SD and were analyzed using repeated measures 1-way ANOVA with Dunnett’s multiple comparisons test. (D) Representative flow cytometry plots and quantification of ven-γδ T cell cytotoxicity against primary AML blasts from relapsed or newly diagnosed patients (n = 12 donors). Representative plots from 1 donor sample are shown. Cytotoxicity was assessed by annexin V/ 7-aminoactinomycin D (7-AAD) staining after 12 hours of coculture at a 1:1 E:T ratio. Data were analyzed using Wilcoxon’s matched pairs signed-rank test. (E) Schematic of cytotoxic assay using γδ T cells freshly derived from peripheral blood mononuclear cells (PBMCs) of relapsed or newly diagnosed patients with AML. (F) Cytotoxicity of patient-derived ven-γδ T cells against autologous AML blasts from relapsed AML patients (n = 5) and newly diagnosed AML patients (n = 4), assessed after 12 hours of coculture at a 4:1 E:T ratio. Data were analyzed using 2-tailed paired Student’s t test (B and F). *P < 0.05; **P < 0.01; ***P < 0.001; ****P < 0.0001.
We conducted killing assays assessing 4 additional contexts: ex vivo pretreating of γδ T cells that we expanded from multiple healthy donors, using a diverse set of AML cell lines as target cells, using AML patient-derived primary AML blasts as target cells, and using primary γδ T cells from treatment-naive and relapsed AML patients targeting autologous AML blasts. Across these various assays, we consistently found that pretreating γδ T cells with venetoclax significantly boosted their cytotoxic capacity against AML target cells (Figure 2, C–F, and Supplemental Figure 1, A–C). A similar enhancement was also observed in Vδ1 γδ T cells, in which 1 μM venetoclax pretreatment increased cytotoxicity against KG-1α, MV4-11, and THP-1 cells (Supplemental Figure 2A). Importantly, this enhanced cytotoxicity was retained after cryopreservation and thawing of venetoclax-conditioned γδ T cells, supporting the feasibility of incorporating venetoclax conditioning into an off-the-shelf manufacturing workflow (Supplemental Figure 2B).
Notably, an RNA-seq analysis and a set of confirmatory follow-up analyses using flow cytometry showed trends consistent with increased cytotoxic capacity for the ven-γδ T cells, including significantly elevated levels of natural killer group 2D (NKG2D), DNAX accessory molecule-1 (DNAM-1), and γδ TCR (Figure 3, A–C). Moreover, the ven-γδ T cells showed stronger activation upon AML cell contact than the DMSO control group cells, as evidenced by elevated expression of CD69, CD25, and IFN-γ for analyte cells collected at the end of the assay (Figure 3D). These results demonstrate proof of concept that our ex vivo pretreatment of γδ T cells with venetoclax mirrors the increased anti-AML cytotoxic capacity known for a similar pretreatment of αβ T cells.
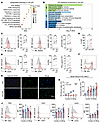 Figure 3
The venetoclax pretreatment promotes γδ T cell expansion and decreases exhaustion. (A) Representative upregulated gene set enrichment analysis pathway enrichment analysis in ven-γδ T cells. NES, normalized enrichment score. (B) Representative GO enrichment results for molecular function (MF), biological process (BP), and cellular component (CC) categories. (C) Median fluorescence intensity (MFI) of activating receptors, including natural killer group 2D (NKG2D), DNAX accessory molecule-1 (DNAM-1), and γδ TCR, on γδ T cells treated with dimethyl sulfoxide (DMSO) or venetoclax (1 μM, 18 hours), assessed by flow cytometry. Each paired symbol represents 1 donor (n = 6). (D) Expression of activation markers CD25 and CD69 on ven-γδ T cells after coculture with KG-1α cells, and IFN-γ levels in culture supernatants measured by ELISA. Each paired symbol represents 1 donor (n = 8). (E) Flow cytometric analysis of Ki-67 expression in γδ T cells after venetoclax treatment. Each point represents an independent donor (n = 7). (F and G) Flow cytometry plots of EdU incorporation (F) and representative immunofluorescence images of EdU and Hoechst 33342 staining (G). Images and plots are representative of 3 independent donor experiments. Scale bars: 50 μm. (H–J) Serial killing assays using γδ T cells expanded with DMSO or venetoclax (400 nM) and repeatedly challenged with OCI-AML3 cells. (H) AML viability by luminescence (n = 3 donors). (I) Absolute γδ T cell counts across killing cycles (n = 5 donors). (J) MFI of inhibitory receptors TIM3, LAG-3, and TIGIT during serial killing (n = 4 donors). Data represent the mean ± SD and were analyzed by 2-tailed paired Student’s t test. Data represent mean ± SD. Paired 2-tailed Student’s t test was used unless otherwise indicated. *P < 0.05; **P < 0.01; ***P < 0.001; ****P < 0.0001.
The venetoclax pretreatment promotes γδ T cell proliferation and decreases exhaustion. The aforementioned studies examining αβ T cells have repeatedly emphasized positive impacts of a venetoclax pretreatment on proliferation and expansion (9, 31), so it was notable that our RNA-seq analysis of ven-γδ T cells indicated elevated levels for genes with functional annotations related to cell division, the G2M checkpoint, and mitotic spindles, among others (Figure 3, A and B, and Supplemental Tables 4 and 5). We examined the proliferation of ven-γδ T cells with multiple assays: the ven-γδ T cells showed significantly increased proliferation over the DMSO control cells in both 5-ethynyl-2′-deoxyuridine (EdU)/propidium iodide (PI) and calcein AM assays (Figure 3, F and G, and Supplemental Figure 3, A and B), and flow cytometry showed that the ven-γδ T cells had significantly increased expression of the proliferation marker Ki-67 (Figure 3E). Additionally, brief exposure (18 hours) increased γδ T cell expansion, and extended culture with venetoclax further augmented proliferation without compromising viability (Supplemental Figure 3, C–F). Consistent with prior observations in NK cells that venetoclax sensitivity is influenced by activation state (33), activated/expanded γδ T cells showed reduced venetoclax-induced cell death compared with resting γδ T cells (Supplemental Figure 3G). We next assessed antiapoptotic protein expression and found higher myeloid cell leukemia 1 (MCL-1) and BCL-XL levels in activated γδ T cells than in resting cells. Under the same assay conditions, the MCL-1 inhibitor S63845 and the BCL-2/BCL-XL inhibitor navitoclax induced greater cell death than venetoclax at matched concentrations (Supplemental Figure 3, H and I). The activated/expanded γδ T cell population that survives the conditioning window thus displays the metabolic and functional features described below, irrespective of whether differential proliferation among γδ T cell subpopulations contributes to the recovered cell composition.
We subsequently conducted serial killing assays to assess the potential benefits of the venetoclax pretreatment in terms of killing persistence and exhaustion markers. Briefly, compared with control DMSO-γδ T cells, the ven-γδ T cells achieved superior antileukemic activity and higher proliferation across a panel of AML lines in up to 5 rounds of AML cell exposure (Figure 3, H and I, and Supplemental Figure 4, A–C), supporting that the pretreatment promotes the killing persistence of γδ T cells. Notably, the DMSO-γδ T cells showed significantly increased levels of exhaustion markers (e.g., T cell immunoglobulin mucin receptor 3 [TIM3], T cell immunoreceptor with Ig and ITIM domains [TIGIT], lymphocyte activation gene 3 [LAG-3]) compared with ven-γδ T cells, indicating that the venetoclax pretreatment somehow decreases the propensity of γδ T cells to undergo exhaustion after repeatedly engaging target cells for killing (Figure 3J). Further, we found that the venetoclax pretreatment led to a marked increase in the number of γδ T cells with a stem cell–like memory T cell phenotype (CD45RA+CD62L+, CCR7+; Supplemental Figure 4D). These findings establish that the venetoclax pretreatment promotes γδ T cell proliferation and reduces functional exhaustion after the ven-γδ T cells repeatedly engage target AML cells for killing.
The venetoclax pretreatment boosts the in vivo efficacy of a γδ T cell therapy against AML. In light of the clinical data supporting differential γδ T cell abundance and functional phenotypes in the CR versus relapsed AML patients, and encouraged by our discovery that a venetoclax pretreatment boosts γδ T cell activity against AML blasts, we next examined potential in vivo therapeutic benefits from ven-γδ T cells against AML. We established a xenograft model using NOD/Prkdcscid/IL2rgnull (NPG) immunodeficient mice: mice were engrafted with KG-1α-luc cells and were subsequently given adoptive transfer of ven-γδ T cells (2 × 10⁷ cells/mouse, twice at a 2-week interval; recombinant human IL-15 [rhIL-15] 1 μg/mouse, every 3 days), γδ T cells with DMSO pretreatment, or PBS (Figure 4A).
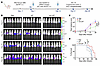 Figure 4
Venetoclax enhances the in vivo efficacy of γδ T cells against AML. (A) Schematic of the experimental procedure. NPG mice were engrafted with 3 × 10⁶ KG-1α-luc cells. One week later, mice were treated with vehicle control, DMSO-γδ T cells, or ven-γδ T cells (2 × 10⁷ cells per infusion, 2 infusions, 2-week interval). KG-1α is an immature AML cell line with complex cytogenetic abnormalities, including del(7) and multiple monosomies, and a reported TP53 alteration. (B) Bioluminescence images of tumor burden in 3 groups. (C) Quantification of bioluminescence imaging values representing tumor burden, n = 7. Data represent mean ± SD. Statistical significance was determined using 2-way repeated measures ANOVA with Tukey’s multiple comparisons test. ****P < 0.0001. (D) Kaplan-Meier survival analysis (n = 7 mice per group). Statistical significance was determined by the log-rank test. **P < 0.01.
Supporting an antileukemia benefit from the venetoclax pretreatment, the extent of KG-1α engraftment was significantly reduced in the ven-γδ T cell group compared with both the γδ T cell and PBS groups (Figure 4, B and C). Consistent with this enhanced leukemia control, mice treated with ven-γδ T cells showed a significantly prolonged survival compared with those receiving DMSO-pretreated γδ T cells or PBS (Figure 4D). To model a clinically applicable regimen, we further tested oral venetoclax in THP-1-luc–engrafted NPG mice randomized to receive PBS, γδ T cells, oral venetoclax, or the combination (Figure 5A). Oral venetoclax plus γδ T cells achieved superior leukemia control over either monotherapy (Figure 5, B and C). Notably, the combination group also exhibited significantly prolonged survival relative to all other treatment groups, supporting an in vivo benefit of combining venetoclax with γδ T cell therapy in this model (Figure 5D).
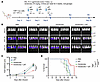 Figure 5
Venetoclax gavage augments the in vivo efficacy of adoptively transferred γδ T cells against AML. (A) Schematic of the experimental procedure. NPG mice were inoculated intravenously with THP-1-luciferase AML cells. Three days after tumor engraftment, mice were randomized into 4 groups: (i) PBS control; (ii) venetoclax alone (75 mg/kg by oral gavage, 5 times per week for 3 weeks); (iii) γδ T cell infusion alone (1 × 10⁷ cells per mouse via tail vein, once every 3 days, total of 3 infusions); and (iv) combination venetoclax + γδ T cells (same venetoclax schedule plus γδ T cell infusions as above). Tumor burden was monitored longitudinally by bioluminescence imaging. THP-1 is a human acute monocytic leukemia (FAB M5) cell line with reported oncogenic NRAS gain-of-function and TP53 alterations. (B) Bioluminescence imaging of mice (n = 10). (C) Quantification of bioluminescence imaging values representing tumor burden (n = 10 mice per group). Data represent mean ± SD. Statistical significance was determined using 2-way repeated measures ANOVA with Tukey’s multiple comparisons test. ****P < 0.0001. (D) Kaplan-Meier survival analysis of THP-1-luc–engrafted NPG mice treated with PBS, γδ T cells, oral venetoclax, or oral venetoclax plus γδ T cells (n = 10 mice per group). Statistical significance was determined by the log-rank test. **P < 0.01; ***P < 0.001; ****P < 0.0001.
Collectively, the results from experiments targeting AML blasts and AML model animals demonstrate that our strategy of pretreating γδ T cells with venetoclax clearly increases their antileukemic activity, to the extent of conferring a therapeutic benefit.
Venetoclax pretreatment enhances mitochondrial abundance and promotes FAO–OXPHOS–linked metabolism in γδ T cells. We next conducted a series of analyses to investigate how the venetoclax pretreatment promotes γδ T cell proliferation and reduces functional exhaustion. We first conducted transmission electron microscopy analysis and observed a significantly higher mitochondria number in ven-γδ T cells, without affecting the morphology of mitochondria (Figure 6A and Supplemental Figure 5, A and B). Further, mitochondrial DNA (mtDNA) quantification showed significantly higher mitochondrial content in the ven-γδ T cells over control cells (Figure 6B), and assessment of mitochondrial mass (by MitoTracker Green) showed a significant increase in ven-γδ T cells (Figure 6, C and D). These findings together support that the venetoclax pretreatment somehow promotes mitochondrial abundance.
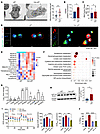 Figure 6
Venetoclax promotes mitochondrial abundance and FAO–OXPHOS–linked metabolism in γδ T cells. (A) Transmission electron microscopy of γδ T cells pretreated with dimethyl sulfoxide (DMSO) or venetoclax. White arrows indicate mitochondria. Scale bars: 2 μm. Mitochondrial number was quantified from more than 3 randomly selected cells per group (n = 3 donors). (B) Mitochondrial DNA content in DMSO- and venetoclax-pretreated γδ T cells (ven-γδ T cells), measured by qPCR for mitochondrially encoded cytochrome c oxidase I (MT-CO1), as a marker of mitochondrial DNA content, relative to β-actin (n = 5 donors). (C) Mitochondrial mass assessed by MitoTracker Green flow cytometry (n = 5 donors). (D) Confocal images and 3D renderings of DMSO- and ven-γδ T cells. Images are representative of 3 independent donor experiments. Red, γδ TCR; blue, Draq5; green, MitoTracker Green. Scale bars: 5 μm. (E) Heatmap of differentially abundant metabolites (P < 0.05) identified by untargeted metabolomics using γδ T cells from 5 donors. Abundances are Z-score–normalized. (F) Pathway enrichment by MetaboAnalyst; main pathways with a P value < 0.05 are shown. (G) Fold-changes of FAO-related genes in ven-γδ T cells versus DMSO-γδ T cells, normalized to β-actin (≥3 donors, triplicate measurements). (H) CPT1A protein by immunoblot (representative of 3 donors) with pooled quantification (n = 6 donors). Mean ± SD. Data were analyzed using Wilcoxon’s matched pairs test. (I) OCR curves after DMSO, venetoclax, etomoxir (Eto) plus DMSO, or venetoclax plus etomoxir (5 μM, 18 hours) treatment, with basal and maximal OCR quantified. Data are representative of 3 independent donor experiments. Oligo, oligomycin; Rot/AA, rotenone and antimycin A; FCCP, carbonyl cyanide p-trifluoromethoxyphenylhydrazone. (J) Cytotoxicity of γδ T cells after the indicated treatments (n = 3). Data represent mean ± SD. Statistical analyses were performed using unpaired, 2-tailed Student’s t test (A and G), paired 2-tailed Student’s t test (B and C), and repeated measures 1-way ANOVA with Tukey’s multiple comparisons test (I and J). *P < 0.05; **P < 0.01; ***P < 0.001; ****P < 0.0001.
We also conducted untargeted metabolomic profiling that revealed substantially increased levels of multiple lipid species (e.g., unsaturated phospholipids, long-chain unsaturated fatty acids) in ven-γδ T cells over DMSO-γδ T cells (Figure 6E and Supplemental Table 6). Additionally, pathway enrichment analysis identified FAO-related metabolic pathways in ven-γδ T cells (Figure 6F). FAO-related transcripts were upregulated (Figure 6G), and carnitine palmitoyltransferase 1A (CPT1A), the rate-limiting enzyme of FAO, was also elevated at the protein level (Figure 6H). Considering these mitochondria and energy phenotypes together, we next monitored mitochondrial respiration in ven-γδ T cells and DMSO-γδ T cells after coculturing with AML blasts. The values for both the oxygen consumption rate (OCR) and spare respiratory capacity were significantly higher in ven-γδ T cells (Supplemental Figure 5C). Notably, despite this increased overall mitochondrial respiration, we detected no change in glycolytic activity as assessed by extracellular acidification rate (Supplemental Figure 5D).
Pursuing the differential OXPHOS profiles alongside the FAO-related changes, we examined ven-γδ T cells and DMSO-γδ T cells after exposure to an inhibitor of the FAO pathway enzyme CPT1A (etomoxir). FAO pathway inhibition attenuated the aforementioned venetoclax pretreatment–induced increases in OCR (Figure 6I) and led to an approximately 40% reduction in the magnitude of the venetoclax pretreatment–induced boost in the cytotoxic capacity of γδ T cells (Figure 6J). Collectively, these results support that the venetoclax pretreatment promotes an FAO–OXPHOS–skewed form of energy metabolism in γδ T cells and moreover that this FAO–OXPHOS–skewed metabolic impact of the venetoclax pretreatment can at least partially account for the increased proliferation and decreased exhaustion observed in ven-γδ T cells.
Venetoclax enhances CLL-1 CAR γδ T cell–mediated cytotoxicity against AML in vivo. Given the in vivo therapeutic benefit we observed for ven-γδ T cells, and considering the numerous advantages that are possible with engineered cell therapies like CAR T cells, we next explored whether a venetoclax pretreatment can increase the efficacy of therapeutic CAR γδ T cells. Specifically, we engineered CAR γδ T cells targeting CLL-1, a surface antigen that is highly expressed on THP-1 cells (34). Mice engrafted with THP-1 cells were given PBS or treated with adoptive transfer of these CAR γδ T cells or venetoclax-pretreated CAR γδ T cells (Figure 7A).
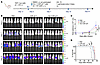 Figure 7
Venetoclax enhances the in vivo efficacy of CLL-1 CAR γδ T cells against AML. (A) Schematic of the experimental procedure. NPG mice were intravenously engrafted with 2 × 10⁶ THP-1-luc cells. Three days later, mice were treated with vehicle control, DMSO-CAR γδ T cells, ven-CAR γδ T cells (5 × 10⁶ CAR+ cells per mouse). (B) Bioluminescence images of tumor burden in 3 groups. (C) Quantification of tumor burden, n = 7 mice per group. Data represent mean ± SD. Statistical significance was determined using 2-way repeated measures ANOVA with Tukey’s multiple comparisons test. **P < 0.01; ***P < 0.001. (D) Kaplan-Meier survival analysis (n = 7 mice per group). Statistical significance was determined by the log-rank test. **P < 0.01; ***P < 0.001.
Consistent with our findings from the earlier in vivo efficacy experiments using adoptive transfer of γδ T cells (i.e., nonengineered), our ven-CAR γδ T cells led to a significantly reduced extent of AML engraftment compared with both the PBS and CAR γδ T cell groups (Figure 7, B and C). Ven-CAR γδ T cells also showed a significantly prolonged survival compared with those receiving DMSO-pretreated CAR γδ T cells or PBS (Figure 7D). These results collectively establish that the ex vivo venetoclax pretreatment boosts the efficacy of both therapeutic γδ T cells and therapeutic CAR γδ T cells.


Copyright © 2026 American Society for Clinical Investigation
ISSN: 0021-9738 (print), 1558-8238 (online)